

If your knee has hurt for months, a knee MRI can feel like the obvious next step. For most people whose knee pain came on gradually after age 45, it is not the first step, and frequently it is not needed at all. A weight-bearing X-ray and a careful hands-on exam usually answer the question a knee MRI is being asked to answer, and they answer it sooner. A scan becomes genuinely useful in a narrower set of situations, and knowing which ones can save you weeks of waiting.
This guide covers what each type of imaging actually shows, when a knee MRI changes what happens next, and what we look at during an evaluation at Regenerative Joint Clinics in Riverdale, GA.
Key takeaways
- For suspected osteoarthritis, a standing (weight-bearing) X-ray is the appropriate first image, not a knee MRI.
- A knee MRI is most useful when the exam and the X-ray disagree, when true mechanical locking is present, or when an acute injury suggests a ligament tear.
- Meniscal tears show up on scans in most older knees, including knees that do not hurt, so a tear on a report is not automatically the source of pain.
- Our Riverdale evaluation uses digital X-ray, fluoroscopy and diagnostic musculoskeletal ultrasound, plus a physical exam and a standardized function score.
- If you already have a knee MRI report, bring it. It still informs the plan even when it was not strictly necessary.
Do you actually need a knee MRI?
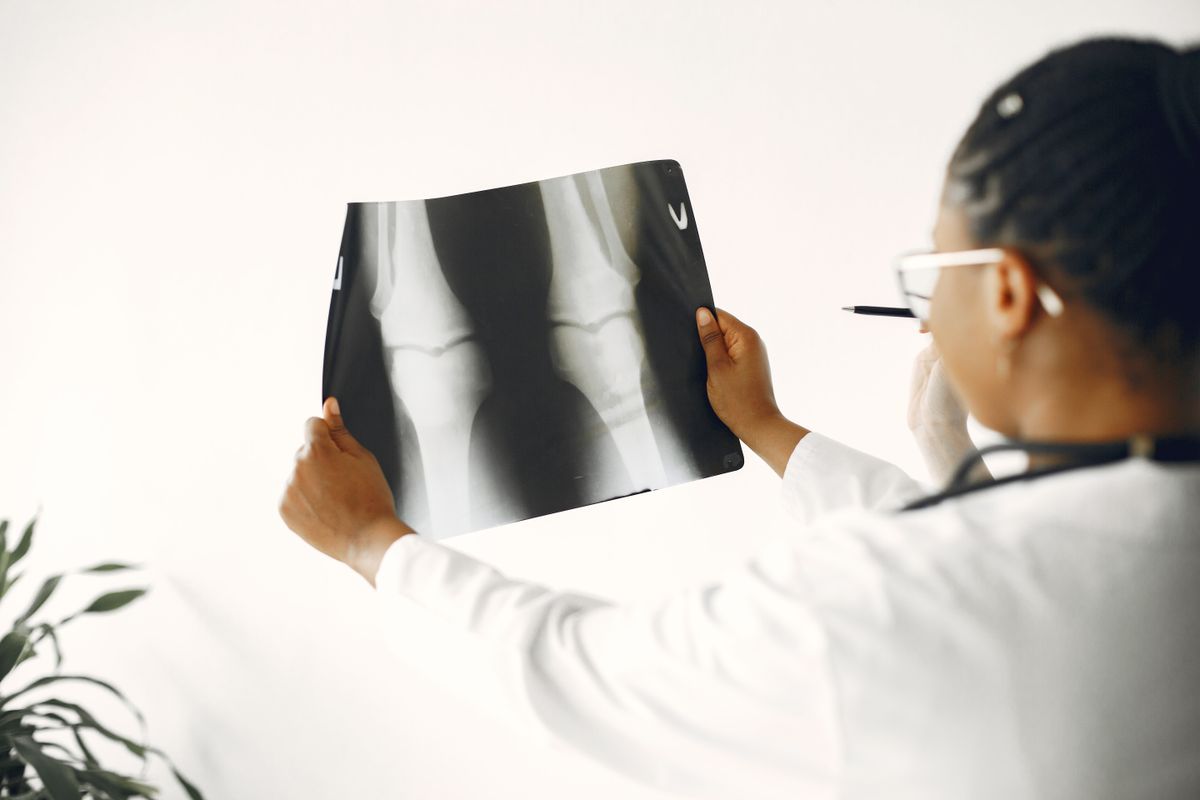
Start with what the two images are good at. An X-ray shows bone. It shows the space between the bones, the spurs that form at the edges of a worn joint, and the alignment of the leg under load. An MRI shows soft tissue: cartilage, menisci, ligaments, tendons and bone marrow changes. Both are useful, but they are answering different questions, and only one of them is the right opening move for chronic knee pain.
Professional guidance here is unusually direct. The American College of Radiology’s Appropriateness Criteria for chronic knee pain place radiographs first and state that MRI without contrast is usually not indicated when radiographs are already diagnostic of osteoarthritis, unless the symptoms are not explained by what the X-ray shows or the treatment being considered requires more information. Choosing Wisely Canada’s orthopaedics list, written with the Arthroscopy Association of Canada, puts it more plainly still: do not order a knee MRI when weight-bearing X-rays already demonstrate osteoarthritis and the symptoms fit osteoarthritis, because the MRI rarely adds information that changes diagnosis or treatment.
That is the short answer for a large share of people who ask about a knee MRI. If you are in your fifties or older, the pain built up over months or years, it is worse going down stairs or after sitting, and it eases with movement, the picture is already familiar. A standing X-ray confirms it. The knee MRI, in that scenario, mostly confirms what everyone already suspected while adding a wait and a bill.
What a weight-bearing X-ray shows that a knee MRI can miss
There is one detail that surprises people: an MRI is usually taken lying down, and a knee lying down is not a knee doing its job. Cartilage loss is measured by how much the joint space narrows when your body weight is pressing the bones together. Take that load away and the gap can look better than it behaves.
Standing radiographs reflect medial and lateral compartment cartilage loss more accurately than supine ones, and a weight-bearing flexion view assesses the back of the joint better still. This is why the phrase in the guidance is always “weight-bearing” and not simply “X-ray.” A supine film underestimates the same joint a standing film reads correctly. So does a knee MRI performed lying flat, at least for the specific question of how much room is left in the joint under load.
None of this makes a knee MRI a bad test. It makes it the wrong opening test for a mechanical, load-related problem. If you want to see what is happening to a joint that hurts when you walk on it, look at the joint while it is being walked on.
When does a knee MRI actually change the plan?
A test earns its place when the result would change what happens next. By that standard there are a handful of situations where a knee MRI clearly does.
The first is true mechanical locking. Not stiffness, and not the vague catching sensation that comes and goes: a knee that physically will not straighten, or that jams mid-motion and has to be worked loose. A displaced bucket-handle meniscal tear is the classic cause, and it is a structural problem that a knee MRI can map before anything else is decided.
The second is an acute injury with a plausible mechanism. A pivot, a pop, immediate swelling within a few hours, and a knee that feels like it is giving way underneath you is a different story from gradual wear. Ligament injuries are exactly what MRI is good at, and here a scan is doing real diagnostic work rather than confirming the obvious.
The third is a mismatch. Your symptoms are severe, or they are in an unusual place, or they simply do not match what the X-ray shows. That gap is the exact circumstance the radiology criteria carve out, and it is a good reason to look further. The American Medical Society for Sports Medicine frames its version around anterior knee pain: hold off on a knee MRI when there are no mechanical symptoms and no effusion, unless a proper rehabilitation program has been completed without improvement, and reconsider if pain persists, swelling keeps returning, or locking and painful clicking appear while the radiographs stay unrevealing.
The fourth is surgical planning. If an operation is genuinely on the table, the surgeon may want the detail. That reasoning does not apply to non-surgical care, which is worth saying out loud, because a scan ordered to plan an operation you are not having is a scan that will not change your treatment.
Why a torn meniscus on a knee MRI may not be your problem
This is the part that reframes the whole conversation, and it comes from one of the more quietly influential studies in joint medicine. Researchers in the Framingham study imaged the knees of 991 people aged 50 to 90, chosen from the general population rather than from a clinic, so the sample was not selected for having knee trouble.
Among people with radiographic osteoarthritis, a meniscal tear turned up in 63% of those with frequent knee pain, aching or stiffness and in 60% of those with none of it. Sixty-one percent of everyone found to have a tear had felt no pain, aching or stiffness at all in the previous month. Prevalence climbed steadily with age, from 19% in women aged 50 to 59 up to 56% in men aged 70 to 90.
Read that again in practical terms. Past a certain age, a person without knee pain is nearly as likely to have a meniscal tear on a scan as a person with it. So when a knee MRI report lists a tear, the finding is real, but on its own it does not establish that the tear is what hurts. Degenerative meniscal changes are close to a normal feature of an aging joint, in the same way grey hair is.
The risk is a treatment aimed at an incidental finding while the actual driver, usually the osteoarthritis around it, goes unaddressed. Our fuller discussion of meniscus tear treatment without surgery covers how we separate a tear that matters from one that is simply present.
What imaging do we use at our Riverdale clinic?
We do not operate an MRI scanner, and for the way we work, that turns out to matter less than patients expect. Our evaluation is built around three imaging tools plus the exam itself.
Digital X-ray is the starting point, for the reasons above. Fluoroscopy, using a C-arm, gives live imaging rather than a still frame, which is what allows an injection to be placed inside the joint under direct visualization instead of by feel. Diagnostic musculoskeletal ultrasound covers much of the soft-tissue ground people assume requires a knee MRI: it is excellent for effusion, for bursitis, for superficial tendon and ligament problems and for Baker’s cysts, and unlike any scan it is dynamic, so we can move the joint and watch what happens. Published comparisons against MRI put ultrasound’s agreement for detecting knee effusion at around 93% sensitivity with 100% specificity.
That same C-arm is also what makes an in-office knee arthrogram possible, a study in which contrast is injected into the joint so that its surfaces show up on X-ray. It is a step we take when the inside of the joint needs to be seen more clearly than a plain film allows.

Alongside the images we use a physical examination and the WOMAC index, a standardized score for pain, stiffness and daily function. That last piece is worth dwelling on, because it measures the thing you actually came in about. A knee MRI describes tissue. WOMAC describes whether you can get up from a chair, climb your own stairs and sleep through the night, and it gives us a number to compare against three months from now.
You can read more about how we use diagnostic musculoskeletal ultrasound and why image-guided injections are placed the way they are.
How imaging fits into the Targeted Restoration Protocol
Imaging exists to answer questions that change the plan, so it helps to know what the plan can be. The Targeted Restoration Protocol combines guided injections, unloading bracing, physical therapy and lifestyle guidance, with the mix set by what the joint looks like and how it is functioning.
A standing X-ray showing joint space narrowing tells us where load is concentrated, which is what an unloader brace is designed to shift. Ultrasound showing an effusion may point toward drawing off fluid before injecting, which is a decision made in the room. Fluoroscopy then guides the injection itself. Notice that a knee MRI does not sit anywhere in that chain for a typical osteoarthritic knee: the choices are driven by load, alignment, swelling and function, and those are answered by weight-bearing images and a hands-on exam.
Where we do want more information, we say so. If your presentation suggests something the X-ray and ultrasound cannot settle, that is a conversation to have about advanced imaging rather than a box to tick beforehand.
What if you already have a knee MRI report?
Bring it. Whether or not it was necessary, it is information, and there is no sense repeating an image you already have. Bring the report and the disc or portal link if you have them, since the radiologist’s written impression and the actual images are not interchangeable.
What we will not do is treat the report as the diagnosis. A knee MRI report on an older knee often reads alarmingly: degenerative tearing, chondral thinning, marginal osteophytes, a small effusion, a Baker’s cyst. Much of that is the expected appearance of a joint that has been used for sixty years. The findings that matter are the ones that line up with where it hurts, what makes it worse and what the exam reproduces. If your report mentions fluid on the knee or describes the joint as bone on bone, those pages explain what the terms mean and what can be done without surgery.
Knee imaging at a glance
| Imaging | Best at | Limitations | Typical first use |
|---|---|---|---|
| Weight-bearing X-ray | Joint space under load, bone spurs, alignment, arthritis grading | Does not show cartilage, menisci or ligaments directly | First image for gradual-onset knee pain |
| Diagnostic musculoskeletal ultrasound | Effusion, bursitis, superficial tendons and ligaments, Baker’s cysts, dynamic movement, injection guidance | Cannot see inside the joint past bone; operator dependent | Soft-tissue and swelling questions, in the same visit |
| Fluoroscopy (C-arm) | Live imaging during a procedure so an injection lands where intended | Procedural, not a standalone diagnostic scan | Guided injections |
| Knee MRI | Menisci, cruciate ligaments, cartilage detail, bone marrow changes | Taken lying down; finds age-related changes that may not be causing symptoms | Locking, acute ligament injury, symptom and X-ray mismatch, surgical planning |
Frequently asked questions about knee MRI
Is a knee MRI better than an X-ray?
Neither is better in general, because they show different tissue. A knee MRI shows soft tissue in far more detail. A weight-bearing X-ray shows what the joint does under your body weight, which is the relevant question for osteoarthritis and the one an MRI taken lying down answers less well. For gradual knee pain, the X-ray comes first.
Will insurance cover a knee MRI?
Coverage depends on your plan, and many plans require prior authorization for advanced imaging, which is one practical reason clinicians document the exam and the X-ray first. Check with your insurer about your own benefits before scheduling. Coverage for treatment is a separate question from coverage for imaging, and we are happy to walk through both.
Can a knee MRI show arthritis?
Yes, and in some ways in more detail than an X-ray, including cartilage thinning and bone marrow changes. It is still not the first choice for diagnosing osteoarthritis, because a standing X-ray plus your history and exam usually establishes it, and the extra detail rarely changes the treatment that follows.
How long should I wait before asking about a scan?
There is no single number, and some situations should not wait at all: a knee that locks, that gives way, that swelled rapidly after an injury, or that will not bear weight deserves prompt evaluation. For knee pain that has built up slowly, get evaluated rather than watching the calendar. The exam and the X-ray come first either way, and they determine whether a knee MRI would tell anyone anything new.
Do I need a referral to be seen at Regenerative Joint Clinics?
Many patients book directly, though some insurance plans require a referral before they will cover a specialist visit, so it is worth checking your own plan. We cover this in detail in our guide on whether you need a referral to see an orthopedic doctor.
Get your knee evaluated in Riverdale, GA
If your knee has been hurting and you are unsure whether a knee MRI is the right next step, an evaluation is the faster way to find out. We will examine the joint, take weight-bearing images, use ultrasound where it helps and tell you plainly whether more imaging would change anything. You can see what to expect at your first visit before you come in.
Regenerative Joint Clinics is at 483 Upper Riverdale Road SW, Suite F, Riverdale, GA 30274. Call (470) 895-0610, email contact@regenerativejointclinics.com, or get in touch here to schedule. Appointments are required; we do not take walk-ins.
Medical disclaimer: this article is general education about knee imaging and is not medical advice, not a diagnosis, and not a substitute for an in-person evaluation. Individual results vary and no outcome is promised or implied. Talk with a qualified healthcare provider about your own situation before starting, changing or stopping any treatment.



