Weight loss for knee pain works through plain mechanics, not willpower. Every pound you carry arrives at the knee several times over with each step you take. In a Wake Forest University study published in Arthritis & Rheumatism, researchers put 142 older adults with knee osteoarthritis through three-dimensional gait analysis and found that each pound of weight lost produced roughly a four-fold reduction in the load on the knee per step. Ten pounds off your frame is about forty pounds off the joint, on every step, across the thousands of steps you take in an ordinary day.
That is the honest short answer, and it is why weight comes up in almost every osteoarthritis guideline written. It is also incomplete. Weight comes off slowly. Knees hurt now. And losing weight is genuinely harder when walking is the thing that hurts. So this guide covers what the research actually measured, how much loss is enough to be worth the effort, and what you can do about the load on your knee while the slower work is happening.
The four-to-one rule behind weight loss for knee pain
The figure above comes from Messier and colleagues at Wake Forest, published in the July 2005 issue of Arthritis & Rheumatism. Their measurement was precise: a body-weight reduction of one kilogram was associated with a 40.6 newton drop in peak compressive force at the knee. Their own summary of it reads, “each pound of weight lost will result in a 4-fold reduction in the load exerted on the knee per step during daily activities.”
Multiply that across a day. A moderately active adult takes somewhere in the range of five to seven thousand steps. At four pounds of relief per step per pound lost, ten pounds of weight loss removes tens of thousands of pounds of cumulative load from the joint over the course of a single day. That accumulation is the whole point. A knee does not fail because of one heavy step. It wears because of a great many ordinary ones.
This is also why weight loss for knee pain tends to produce results that feel disproportionate to the number on the scale. Patients often describe losing what sounds like a modest amount and noticing a real difference on stairs and slopes. The scale moved a little. The load on the joint moved a lot.
What happened when researchers actually made it happen
Ratios are one thing. An eighteen-month randomized trial testing weight loss for knee pain is another. The IDEA trial, published in JAMA in 2013, enrolled 454 overweight and obese adults aged 55 and over who had knee pain and X-ray evidence of osteoarthritis. Participants were assigned to diet plus exercise, diet alone, or exercise alone, and 399 of them finished.
The diet-plus-exercise group lost an average of 10.6 kg, about 11.4 percent of body weight. The exercise-only group lost 1.8 kg. Three results are worth reading closely:
- Pain. On a 0 to 20 scale, the diet-plus-exercise group reported 3.6 at eighteen months, against 4.7 for exercise alone and 4.8 for diet alone. Combining the two beat either one by itself.
- Joint load. Knee compressive force averaged 2,487 N in the diet group against 2,687 N in the exercise group, a 200 N difference per step.
- Inflammation. IL-6, an inflammatory marker in the blood, fell further in both weight-loss arms than in the exercise arm.
That last point matters more than it might appear. Fat tissue is not inert padding. It is metabolically active and releases inflammatory signals into the bloodstream, which is why weight affects joints that carry no body weight at all, such as the hands. So weight loss for knee pain is doing two separate jobs at once: taking mechanical load off the joint, and lowering the inflammatory background it sits in.
How much weight loss for knee pain is enough?
Less than most people assume. The 2019 osteoarthritis guideline from the American College of Rheumatology and the Arthritis Foundation, published in Arthritis Care & Research, treats weight loss as a first-line measure for knee osteoarthritis and points to roughly 5 percent of body weight as the threshold where people begin to notice a change in pain. For a 200-pound adult, that is ten pounds.
Benefit from weight loss for knee pain does keep climbing past that point, which is what the IDEA numbers show. But the first five percent is where the effort starts paying for itself, and framing the target that way is usually more useful than an aspirational number that never gets reached. Ten pounds is a target. Sixty is a wish.
The half of the load story almost nobody mentions
Here is the gap in nearly every article written on this subject. They all reduce weight loss for knee pain to the instruction “lose weight,” which is advice about something that takes months and depends on a great deal outside a clinic’s control. Meanwhile the knee hurts today.
Load on a knee has two levers, not one. Body weight is the patient-side lever, and it is slow. The clinic-side lever is mechanical, and it works immediately: an unloader knee brace is engineered to shift force away from the worn side of the joint and onto the side that still has cartilage to spare. It does not care how long your weight-loss plan takes. It changes the force distribution the day it is fitted.
Both levers act on the same variable, which is why weight loss for knee pain and bracing belong in the same conversation. That is the useful insight. A patient who loses ten pounds while wearing a properly fitted offloading brace is attacking joint load from two directions at once, and the two effects add rather than compete.
Why we look at your X-ray before we talk about your weight
At our Riverdale clinic there is a specific reason the imaging comes first, and it is the part of this discussion that is genuinely clinic-side rather than something you can read on a general health site.
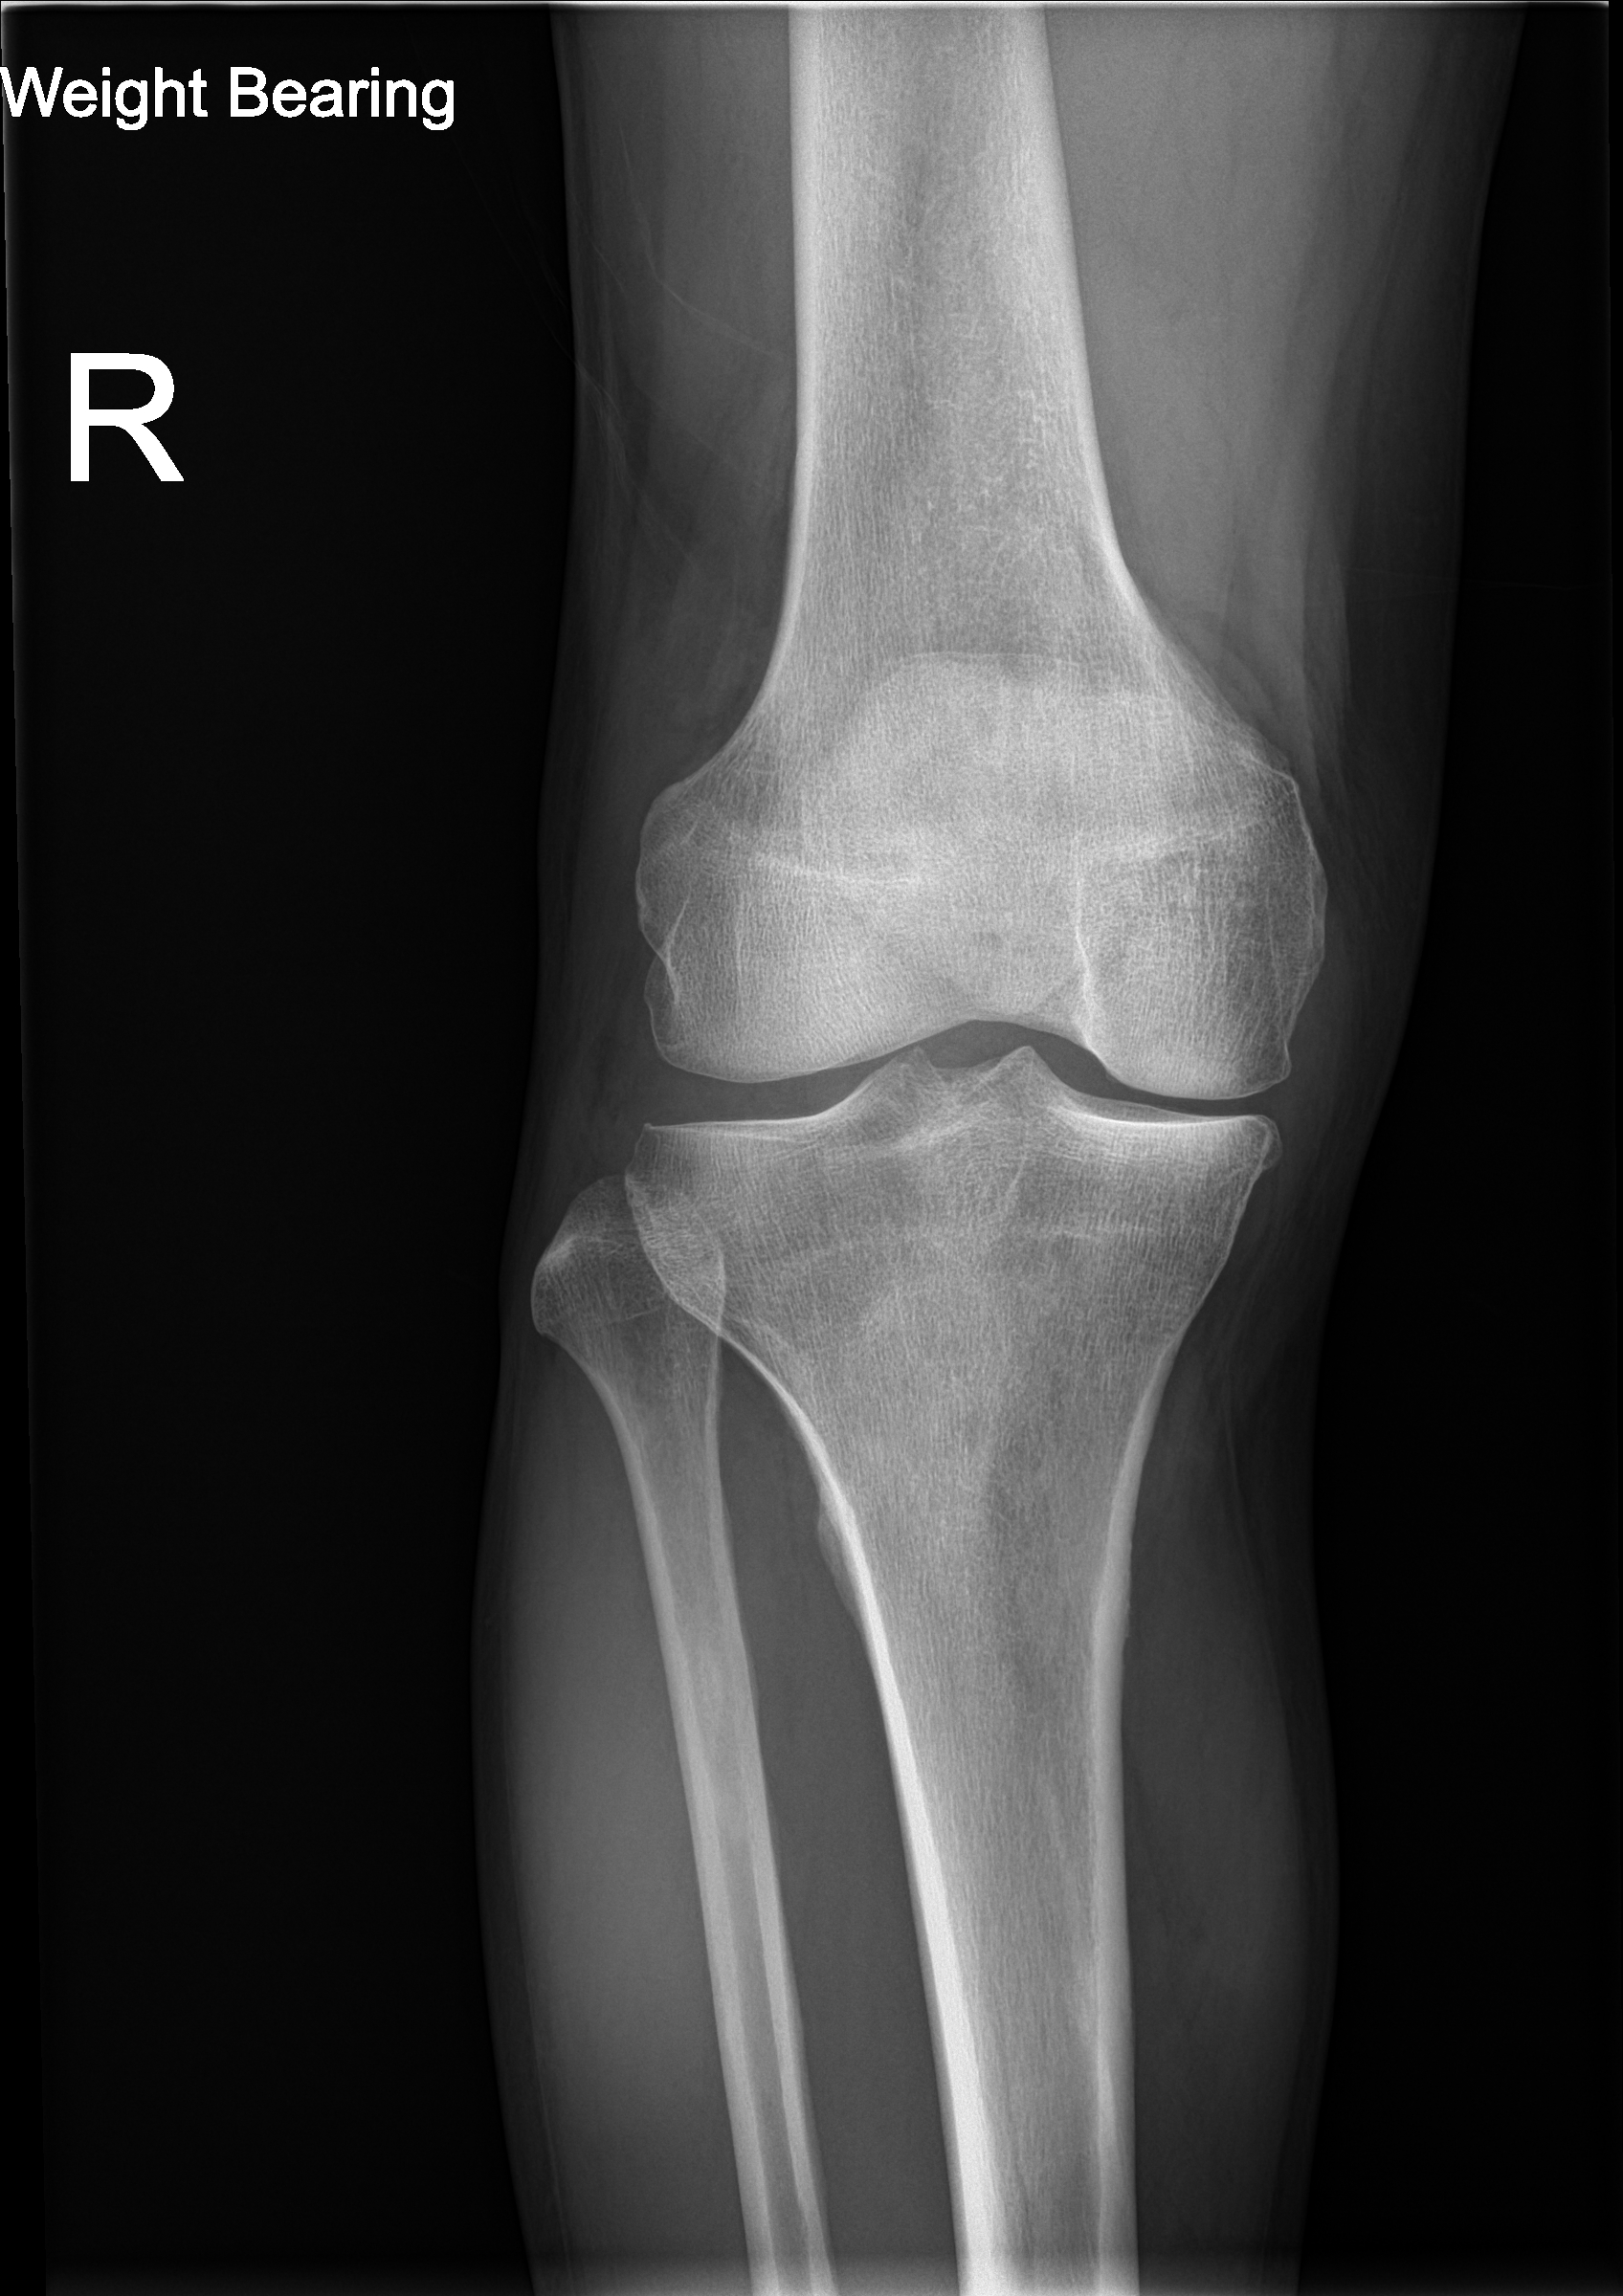
Osteoarthritis is rarely evenly distributed. Most knees wear on one side, usually the inner (medial) compartment, and a weight-bearing X-ray shows which. That single fact changes the plan. If the wear is concentrated on one compartment, an unloader brace has somewhere to move the load to, and bracing becomes a serious part of the strategy alongside weight. If the joint is worn broadly across compartments, a brace has far less to offer, and the plan leans harder on injections, activity changes and the slower work on body weight.
So the honest version of the advice is conditional. Weight loss for knee pain helps essentially everyone, because it reduces total load and background inflammation regardless of where the wear sits. Bracing helps some people a great deal and others hardly at all, and an X-ray is what separates the two groups. Understanding where your knee sits in the stages of osteoarthritis is part of the same conversation.
Weight loss for knee pain when walking is the thing that hurts

This is the real obstacle, and it deserves a straight answer rather than encouragement. The standard advice is to walk more. If walking is what triggers your pain, that advice is a closed loop.
Two things break that loop. The first is choosing activity that produces less knee load per unit of effort. Water-based exercise is the clearest example, because buoyancy removes most of the joint load while leaving the cardiovascular work intact. Stationary cycling with the seat set high enough to avoid deep knee flexion is another. Our guide to low-impact exercise that protects joints covers the practical options in more detail, and there is a separate set of exercises specifically for knee osteoarthritis aimed at the quadriceps, since a stronger quad absorbs load the joint would otherwise take.
The second is treating the pain enough to make movement possible. This is the part people skip, and it is backwards. Getting a painful knee comfortable enough to walk on is often what makes weight loss for knee pain achievable in the first place, rather than something to attempt only after the weight is gone.
On the eating side, the honest note is that structured weight management belongs with your primary care physician, who can look at medications, thyroid function and everything else that affects it. What we can say is that the diet pattern with the most support for joint symptoms is broadly anti-inflammatory, and our guide to foods that support joint health is a reasonable starting point.
Where injections fit while weight loss for knee pain is underway
Weight loss takes months. That interval is where non-surgical treatment does its work, and it is the main reason our knee pain treatment program in Riverdale, GA does not treat weight as a prerequisite for anything.
Fluoroscopically guided hyaluronic acid gel injections supplement the joint’s own lubricating fluid and are typically given as a single injection or a short series. Cortisone can settle an acutely inflamed, swollen knee quickly, which is useful when a flare is what is stopping you moving, though its effect is shorter-acting and the frequency is clinically limited. Platelet-rich plasma (PRP) is an option in selected cases. If the knee is holding excess fluid, drawing that fluid off can relieve pressure on its own.
On cost, the components of our Targeted Restoration Protocol, including diagnostics and gel injections are covered by most major medical insurance plans and Medicare. Bracing coverage depends on your plan and is confirmed before anything is ordered. PRP is the exception and is usually treated as elective rather than covered. Our insurance page sets out what to expect, and Pathways payment plans are available where coverage falls short.
What weight loss for knee pain will not do
Two corrections, because overselling weight loss for knee pain helps nobody.
Weight loss for knee pain does not regrow cartilage. Cartilage that has worn away does not come back because you lost weight. What changes is the load on what remains, the inflammatory environment around it, and in most cases the pain. Slowing a problem and reversing it are different claims, and only the first one is supported.
And it is not a substitute for finding out what is actually wrong. Knee pain in an adult who is overweight gets attributed to weight reflexively, sometimes at the cost of missing a meniscus tear, a Baker’s cyst or an inflammatory arthritis that needs entirely different management. Weight is a contributing factor. It is not automatically the diagnosis.
Common questions
How quickly does weight loss for knee pain make a difference?
Most people who report a change describe it somewhere in the first five to ten pounds, and often notice it first on stairs and inclines rather than on level ground, because those are the movements that multiply knee load the most. The larger trial results were measured at eighteen months, so the full effect is a long arc rather than a quick one.
Does weight loss for knee pain help if I already have severe arthritis?
Yes, though what it changes is different. In an advanced joint it will not restore what has worn away, but it still lowers the force going through the joint every step and reduces the inflammatory load, and both of those affect day-to-day pain. It also matters for anyone considering joint replacement later, since body weight influences both surgical risk and how a replaced joint holds up.
Is walking bad for arthritic knees?
Generally no, and inactivity is worse. The quadriceps supports the knee, and it weakens quickly when you stop using it, which leaves more of the load on the joint itself. The distinction that matters is between walking that leaves you sore for an hour or two and walking that leaves you swollen the following day. The first is usually fine. The second means the dose was too high.
Should I wait until I have lost weight before getting treatment?
No, and that order tends to work against people. A knee that is too painful to walk on makes weight loss for knee pain considerably harder to achieve. Getting the pain to a level where movement is possible is usually what makes the rest workable.
Do I need an X-ray before starting?
For a knee that has hurt for more than a few weeks, a weight-bearing X-ray is worth doing. It shows how much wear is present and, importantly, where it sits, which is what determines whether offloading bracing is likely to help you. It is a fast study and the appropriate first look for suspected osteoarthritis.
Talking it through
If your knee has hurt for more than a few weeks, changed how you walk, or made stairs something you plan around, that is worth an evaluation regardless of what the scale says, and weight loss for knee pain is only one part of the plan we would build. We will look at the joint, work out where the wear sits, and build a plan that treats load from both directions at once.
Regenerative Joint Clinics is at 483 Upper Riverdale Road SW, Suite F, Riverdale, GA 30274. Call (470) 895-0610, email contact@regenerativejointclinics.com, or get in touch through our contact page to arrange a consultation.
Sources
- Messier SP, Gutekunst DJ, Davis C, DeVita P. Weight loss reduces knee-joint loads in overweight and obese older adults with knee osteoarthritis. Arthritis Rheum. 2005 Jul;52(7):2026-32.
- Messier SP, Mihalko SL, Legault C, et al. Effects of intensive diet and exercise on knee joint loads, inflammation, and clinical outcomes among overweight and obese adults with knee osteoarthritis: the IDEA randomized clinical trial. JAMA. 2013 Sep 25;310(12):1263-73.
- Kolasinski SL, Neogi T, Hochberg MC, et al. 2019 American College of Rheumatology/Arthritis Foundation Guideline for the Management of Osteoarthritis of the Hand, Hip, and Knee. Arthritis Care Res (Hoboken). 2020 Feb;72(2):149-162.
Medical disclaimer: this article is general education and is not medical advice, a diagnosis, or a treatment recommendation for any individual. Results vary from person to person. Talk with a qualified clinician about your own situation before making decisions about your care or starting a weight-management plan.